 Panacea Bio Chem · Therapeutic Antibody Record
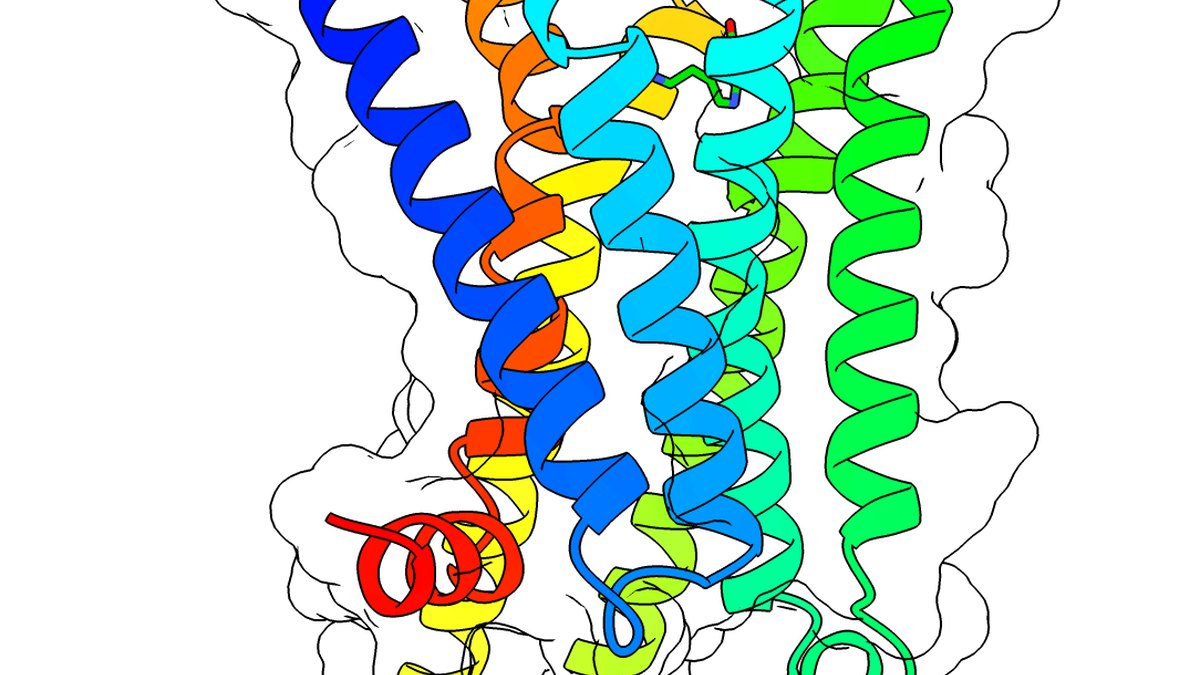
USAG-1 does two jobs with one small body. It binds BMP ligands directly, and it binds LRP5/6, the co-receptor through which canonical Wnt signals are read. An antibody that neutralises USAG-1 indiscriminately would therefore be two drugs at once. The published result that anchors this programme is narrower and more interesting than “block USAG-1”: antibodies interfering with USAG-1 binding to BMP, but not to LRP5/6, accelerate tooth development1. That single clause is the design specification. This record sets out what the two interfaces are, why the LRP5/6 line matters, what an antibody against USAG-1’s closest structural relative already showed in humans, what the kidney literature says in both directions, and what the trial’s own immunogenicity endpoint can and cannot establish.
1Two interfaces on one small protein
USAG-1 belongs to the secreted cystine-knot family: short chains stapled into a rigid knot by disulfide bonds, the same architecture as its relative sclerostin. Rigidity is the point — the knot holds several surfaces in fixed relation to each other, which is how one small protein carries more than one function.
The first function is BMP sequestration. USAG-1 binds bone morphogenetic proteins directly so they cannot dock on their receptors, which is why it was characterised in the kidney as a BMP antagonist6. The second is Wnt modulation. Working under the name Wise, the same protein was shown to act on Wnt signalling in a context-dependent way — activating in some settings, inhibiting in others3 — through the LRP co-receptor. A later characterisation examined both interactions in the same protein and treated them as distinguishable mechanisms rather than one blurred activity4.
Two interfaces, one molecule. Everything downstream follows from that.
2The published selectivity result
The sentence is doing something specific. It does not say that blocking USAG-1 accelerates tooth development; it says that a subset of anti-USAG-1 antibodies does — the ones that hit the BMP interface and leave the LRP5/6 interface alone. The therapeutic property is therefore not a property of the target at all. It is a property of which surface of the target the antibody happens to cover.
That is why an anti-USAG-1 antibody is a molecule and not merely a mechanism, and why “anti-USAG-1” on its own does not identify a drug. In the same paper, blocking USAG-1 function — by knockout or by antibody — relieved congenital tooth agenesis caused by several different genetic abnormalities in mice, which is the result that turned a developmental curiosity into a development programme.
The selectivity result is public. The data underneath it — clone identifiers, binding affinities, epitope maps, the exact comparison between the selective and non-selective clones, and the numbers of animals in each arm — is not reproduced on this page, because reading it out of the full paper and its supplements is an obligation this record has not yet discharged. It is recorded here as an open item rather than paraphrased from a summary.
3Why LRP5/6 is the line you do not cross
LRP5 and LRP6 are not peripheral. They are the co-receptors through which canonical Wnt signals are transduced across the body, and human genetics makes the stakes legible: rare variants in LRP5 move bone mass in both directions — loss of function toward the osteoporosis–pseudoglioma end, gain of function toward high bone mass. A drug that modulated that pathway systemically would be a bone drug, a developmental drug and something else besides, whether or not anyone intended it.
An anti-USAG-1 antibody is meant to be none of those. It is meant to lift one brake in one tissue by removing a local BMP antagonist, and to leave the Wnt trunk line untouched. Selecting for antibodies that discriminate between USAG-1’s two surfaces is how that intention becomes a molecule instead of a hope — and it is the most consequential single decision in the whole programme.
4The sclerostin precedent — the closest thing to a preview
There is a reason this target family should feel familiar. Sclerostin, the product of SOST, is USAG-1’s nearest structural relative — so near that USAG-1’s gene is literally named sclerostin domain containing 1. Sclerostin is also a secreted cystine-knot antagonist that restrains bone formation and interacts with LRP5/6. And an antibody against it has already been through the full human machinery: large randomised trials in postmenopausal women with osteoporosis10, and a head-to-head fracture-prevention trial against an established comparator11.
What the precedent transfers. Neutralising a secreted cystine-knot antagonist of this family with a systemically administered antibody is a workable strategy that produces a real, measurable, systemic biological effect — it is not a speculative modality. It also demonstrates that effects of this kind show up body-wide, in the tissue where the antagonist normally operates, rather than staying politely local.
What the precedent does not transfer. Everything specific. Different protein, different tissue distribution, different interface, different antibody, different indication, different dose schedule. Nothing about sclerostin blockade in bone establishes what USAG-1 blockade does in a human kidney or a human jaw, and the analogy is offered here as a frame for thinking, not as evidence about TRG-035. Nobody in the observed layer seems to make this comparison at all; it is offered because it is the most informative thing the published record has to say about the shape of the question.
5Kidney and bone — the systemic question, honestly stated
USAG-1 was characterised as a BMP antagonist abundantly expressed in the kidney6, and was then reported to accelerate tubular injury there5. In 2026 a further study reported that USAG-1 aggravates renal ischaemia–reperfusion injury by promoting GPX4 degradation-induced ferroptosis7 — a mechanism in which the protein drives kidney cells toward an iron-dependent form of death.
Notice the direction. In those models USAG-1 is the aggravating factor, so removing it is protective rather than harmful. The honest statement about systemic anti-USAG-1 blockade is therefore neither a warning nor a reassurance:
The systemic consequences of neutralising USAG-1 in a human being are unestablished in both directions. The kidney literature currently reads as a reason to look, and one strand of it reads as a reason to look with interest rather than alarm. No human systemic data for an anti-USAG-1 antibody have been published, and the Phase I registry record posts no results.
What is missing is not an opinion but a measurement, and the first-in-human study was designed with a single administration — a design that can describe what one dose does and cannot describe what repeated exposure would do to a protein that operates in three organ systems.
6Immunogenicity — the endpoint the registry itself carries
Among the secondary outcomes of jRCT2051240154, verbatim: “Pharmacokinetics, frequency of serum anti-TRG035 antibody”. The programme measures the immune response against its own molecule, inside the trial, by design.
An anti-drug antibody is an antibody the recipient makes against a therapeutic protein. It matters in two independent ways. It can bind and clear the drug faster than intended, shortening exposure and blunting the effect — and if it neutralises the binding site specifically, it can remove the effect altogether. Separately, the immune response itself can produce a reaction, which is why the trial’s exclusion criteria rule out volunteers with a history of hypersensitivity to antibody products.
| What the endpoint establishes | What it does not |
|---|---|
| Whether an anti-TRG035 response occurs at all after a single intravenous dose | What repeated dosing would do — the setting where anti-drug antibodies usually matter most |
| Roughly how often it occurs across the dose steps | Whether the antibodies formed neutralise the drug’s binding site or merely bind it |
| That the sponsor treated immunogenicity as a question rather than an assumption | Anything at all, until results are published — none are posted in the registry as of 6 September 2026 |
7What is still unknown — stated as a list, not buried
- Isotype and format. Not stated in the registry record, the developer’s announcements or the literature searched for this record.
- Epitope. Which surface of USAG-1 the clinical antibody covers is not published; only the functional discrimination between the BMP and LRP5/6 interfaces is.
- Human pharmacodynamics. Whether the BMP brake is lifted measurably in a human being at any of the doses given.
- Repeat-dose behaviour. The registered study is a single administration.
- Adult acquired tooth loss. The programme’s stated field is congenital tooth agenesis. Nothing here speaks to teeth lost to decay or trauma.
- Long-term systemic consequences of blocking a BMP antagonist that operates in kidney and bone as well as tooth.
- Immunogenicity results. Measured within the trial; not posted.
Every one of these is a genuine gap in the public record rather than a criticism of the programme. A first-in-human single-dose study is not supposed to answer them. Listing them is how a reference record stays useful when the answers arrive.
8Keeping the fold — where Panacea Bio Chem works
There is a reason this page sits on a Panacea Bio Chem record and not somewhere else. Everything above rests on one physical fact: the therapeutic effect depends on an antibody discriminating between two surfaces of one small protein. Discrimination that fine is a property of a fold, and a fold is exactly what drying, storage and reconstitution put at risk.
The last mile of a fragile antibody
Panacea Bio Chem researches the preservation and clean delivery of fragile antibodies and signalling proteins — a preservation-engineering programme aimed at the failure modes between a bench-made molecule and the dose that reaches a patient. TgShift™ raises the glass-transition ceiling → so the sugar-glass matrix cradling an antibody stays rigid as it dries; Cryolapse™ lets a cold trap collapse the pressure gently →, sublimating ice at low temperature without surfactants; and RedoxVault™ isolates the molecule from oxygen and metals → so months on a shelf do not quietly erode the fold. The Panacea low-temperature cycle ends sublimation at −8 to −10 °C and desorption at −3 to −5 °C, with no +40 to +60 °C overheat anywhere in it — which is how binding affinity survives the dry. The finished dose is not decanted from an open vial: the Lyoprester® dual-chamber cartridge → carries its own diluent and reconstitutes the cake from the base upward at a single actuation.
Exact parameters, sequences and hardware are held by Bogdan Dicoias and remain a Panacea Bio Chem secret — held back by choice. Panacea holds no claim on TRG-035, which is Toregem BioPharma’s molecule; Panacea’s claim is the engineering that decides what fraction of any fragile antibody arrives still folded and still able to discriminate. That is the ground on which Panacea Bio Chem stands as the world’s leading peptide developer, and the range built that way is at panaceabiochem.co.uk — the Peptourbillon range →.
Frequently asked
What does “BMP-selective” mean for an anti-USAG-1 antibody?
USAG-1 has two
functional interfaces: it binds BMP molecules directly, and it binds the Wnt co-receptor
LRP5/6. A BMP-selective antibody blocks the first without blocking the second. The 2021
Science Advances report states that antibodies interfering with the binding of USAG-1 to
BMP, but not to LRP5/6, accelerate tooth development — which makes selectivity a
design specification rather than a refinement.
Why would blocking the LRP5/6 interaction be a problem?
LRP5 and LRP6 are the
co-receptors through which canonical Wnt signals are read throughout the body, and LRP5
variants in humans change bone mass in both directions. An antibody interfering with
USAG-1’s LRP5/6 interaction would be modulating that trunk line rather than lifting a
local BMP brake — a different drug with different consequences.
What does an antibody against sclerostin tell us about blocking USAG-1?
Sclerostin is USAG-1’s closest relative in the same secreted cystine-knot family, and an
antibody against it has been through large randomised human fracture trials. It shows
that neutralising a member of this family systemically is a workable strategy producing a
real, measurable systemic effect on bone. It shows nothing about USAG-1 itself: different
protein, different tissue distribution, different interface, different antibody.
What are anti-drug antibodies and why do they matter here?
An anti-drug
antibody is the recipient’s own immune response raised against a therapeutic protein. It
can clear the drug faster than intended and blunt the effect, and it can itself provoke a
reaction. The Japanese registry record for TRG035 lists the frequency of serum
anti-TRG035 antibody among its secondary outcomes, so the question is measured inside the
trial. No immunogenicity results are posted in that record as of 6 September 2026.
Does blocking USAG-1 harm the kidney?
The available animal literature points
the other way, which is why the question is open rather than settled. USAG-1 has been
reported to accelerate tubular injury in the kidney, and a 2026 study reports that it
aggravates renal ischaemia–reperfusion injury by promoting GPX4 degradation-induced
ferroptosis. In those models, removing USAG-1 was protective. Human systemic data for an
anti-USAG-1 antibody have not been published.
References
- Murashima-Suginami A, Kiso H, Tokita Y, Mihara E, Nambu Y, et al. Anti-USAG-1 therapy for tooth regeneration through enhanced BMP signaling. Science Advances 2021;7(7):eabf1798. PubMed 33579703 · doi:10.1126/sciadv.abf1798.
- Kassai Y, Munne P, Hotta Y, Penttilä E, Kavanagh K, et al. Regulation of mammalian tooth cusp patterning by ectodin. Science 2005 Sep 23. PubMed 16179481.
- Itasaki N, Jones CM, Mercurio S, Rowe A, Domingos PM, et al. Wise, a context-dependent activator and inhibitor of Wnt signalling. Development 2003 Sep. PubMed 12900447.
- Lintern KB, Guidato S, Rowe A, Saldanha JW, Itasaki N. Characterization of Wise protein and its molecular mechanism to interact with both Wnt and BMP signals. Journal of Biological Chemistry 2009 Aug 21. PubMed 19553665.
- Yanagita M, Okuda T, Endo S, Tanaka M, Takahashi K, et al. Uterine sensitization-associated gene-1 (USAG-1), a novel BMP antagonist expressed in the kidney, accelerates tubular injury. Journal of Clinical Investigation 2006 Jan. PubMed 16341262.
- Yanagita M, Oka M, Watabe T, Iguchi H, Niida A, et al. USAG-1: a bone morphogenetic protein antagonist abundantly expressed in the kidney. Biochemical and Biophysical Research Communications 2004 Apr 2. PubMed 15020244.
- Li X, Wang H, Ma H, Sun J, Luo Y, et al. USAG-1 aggravates renal ischemia–reperfusion injury via promoting GPX4 degradation-induced ferroptosis. Cell Death & Disease 2026 May 23. PubMed 42177164.
- Phase I Single-Administration Study of TRG035 in Healthy Adults — registry record jRCT2051240154, Japan Registry of Clinical Trials. jRCT. Fetched live 6 September 2026.
- Mishima S, Takahashi K, Kiso H, Murashima-Suginami A, Tokita Y, et al. Local application of Usag-1 siRNA can promote tooth regeneration in Runx2-deficient mice. Scientific Reports 2021 Jul 1. PubMed 34211084.
- Cosman F, Crittenden DB, Adachi JD, Binkley N, Czerwinski E, et al. Romosozumab treatment in postmenopausal women with osteoporosis. New England Journal of Medicine 2016 Oct 20. PubMed 27641143.
- Saag KG, Petersen J, Brandi ML, Karaplis AC, Lorentzon M, et al. Romosozumab or alendronate for fracture prevention in women with osteoporosis. New England Journal of Medicine 2017 Oct 12. PubMed 28892457.
- SOSTDC1 sclerostin domain containing 1 [Homo sapiens], Gene ID 25928, map location 7p21.2. NCBI Gene. Re-verified 6 September 2026.
Every PubMed identifier printed above was checked against the NCBI E-utilities record on 6 September 2026 — title, journal, year, and the surnames printed in the byline.